
While a bunion and a Morton’s neuroma are two different foot conditions, if they are co-existing, they can sometimes influence the way the forefoot is loaded, causing delays or difficulties in the recovery process.
Starting with the bunion, which medically is known as hallux valgus, changes the position and function of the big toe and first metatarsophalangeal joint. On the other hand, Morton’s neuroma is a painful condition involving one of the common plantar digital nerves, most commonly between the third and fourth toes.
If you present with both conditions, treating the neuroma without considering how the rest of the foot is functioning may not always address the mechanical factors contributing to your symptoms.
This is what this blog is going to analyse:
Can a bunion make it harder for a Morton’s neuroma to settle?
The answer is not as simple as saying that a bunion causes a neuroma, as there is not enough evidence for it. But what we know is that hallux valgus can alter how load is distributed through the forefoot, and this may be relevant when managing a sensitive or irritated interdigital nerve.
What is the relationship between a bunion and a Morton’s neuroma?
As mentioned above, a bunion does not automatically cause a Morton’s neuroma.
That said, both conditions can be influenced by the way forces are distributed through the forefoot.
Indeed, Hallux valgus can change the position of the big toe and first metatarsal, which are sitting more laterally than they should be, and alter normal walking mechanics. We know, in fact, that while walking, the big toes should be the primary driver and taker of the body weight at the toe level, and if pushed to a lateral position, it can’t take such load; therefore, the body weight is then redistributed along the phalangea box and other toes.
But to be more specific, and by following what the data show, we better understand this 2025 systematic review and meta-analysis involving more than 6,000 feet found that hallux valgus was associated with reduced hallux loading when measured inside footwear. But evidence that hallux valgus consistently increases loading beneath the central metatarsals was inconclusive.
And this is important because it gives a distinction between bunion and Morton’s neuroma formation, as neither is the consequence of the other. Basically, the correlation and causation effect. Indeed, foot mechanics are individual.
Your symptoms can be influenced by the shape of your foot, footwear, activity, walking pattern, joint mobility, strength, and how you distribute your body weight while moving.
How can a bunion affect Morton’s neuroma recovery?
Now that we clarify the distinction between the correlation and causation of Morton’s neuroma from hallux valgus, we can dig more into how the bunion can affect Morton’s neuroma recovery.
Morton’s neuroma is a condition that can not be recovered by only exercises or some other external interventions, but, to start with, it needs rest. By rest, we mean reducing stress on the structure involved, not no movement at all.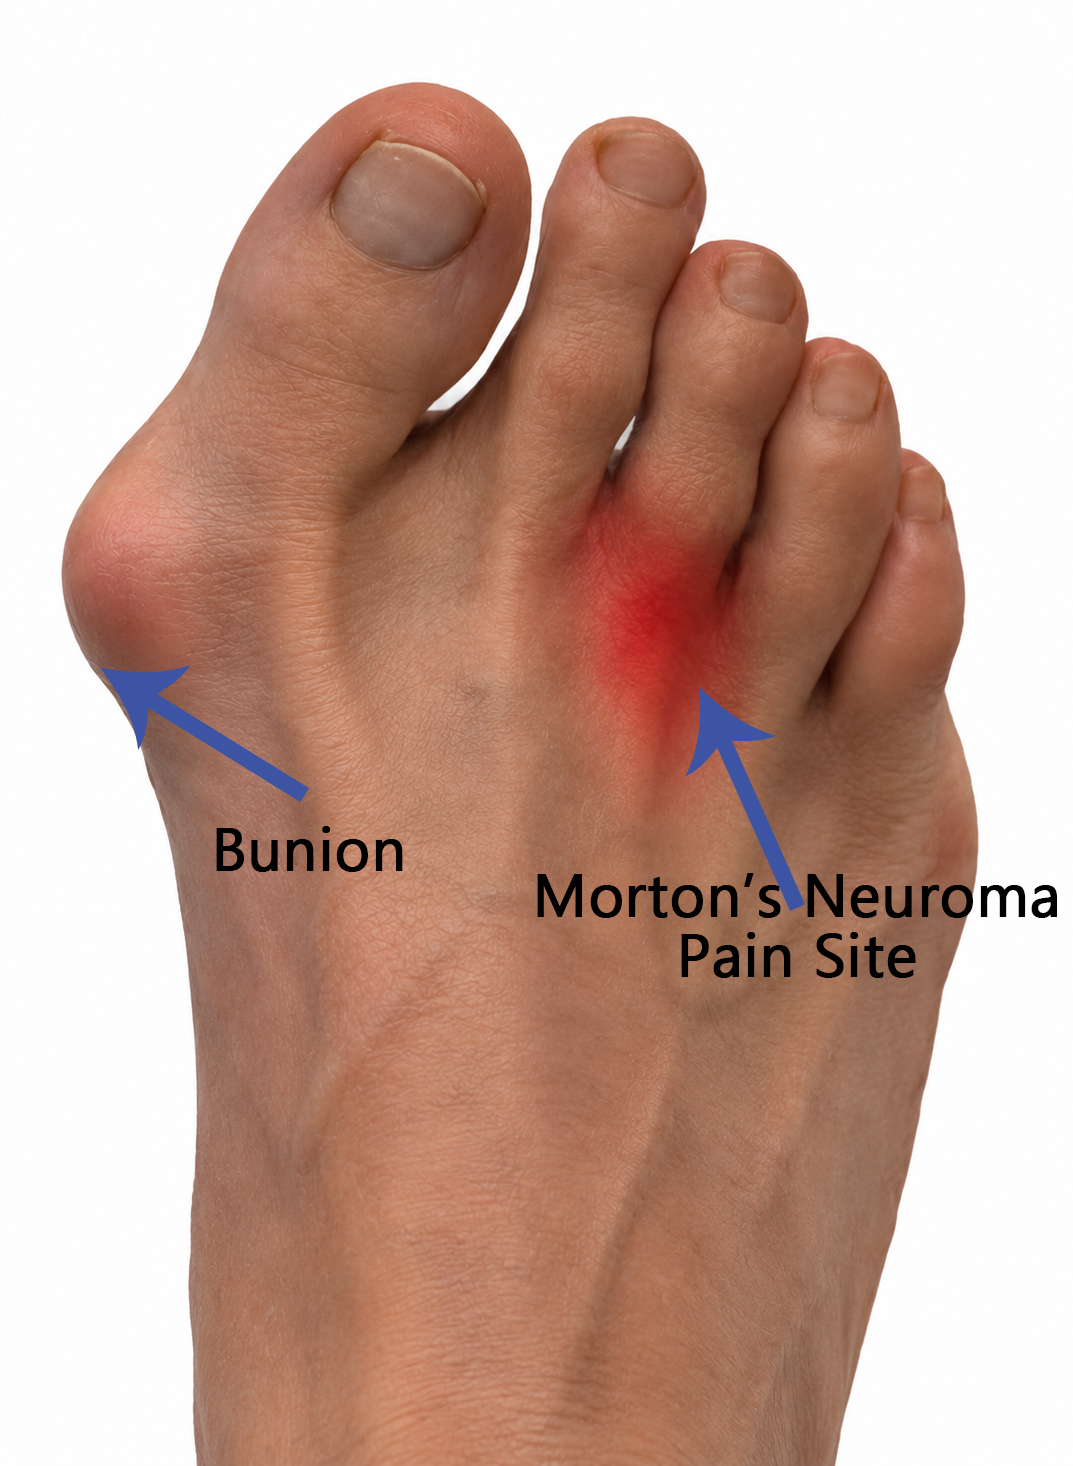
This is why footwear modification and pressure redistribution are commonly used in Morton’s neuroma management.
Therefore, the bunion may become relevant because hallux valgus can alter the way the forefoot loads during walking.
For example, some people with hallux valgus develop a tendency to move the centre of pressure away from the first metatarsophalangeal joint during late stance. Research has demonstrated this lateral shift in people with bilateral hallux valgus.
As a result, if the big toe can not contribute effectively to propulsion, the body may find another way to complete the movement.
So again, this can overload the neuroma site, limiting rest and slowing recovery.
Think about the whole foot, not just the painful spot
When dealing with a painful presentation, I always invite my client to stop focusing only on the painful spot, and start to understand that nothing work in isolation.
Therefore, if someone has a neuroma, it can be tempting to focus entirely on the area between the toes.
But a better approach would be asking:
Why is this area becoming irritated?
The answer is often made up of a combination of factors, which may include:
- Footwear used
- Training load or walking volume
- Forefoot structure or movement
- Possible pre-existing injury
So that’s why treating the neuroma alone may not be enough if the mechanical contributors are still present.
Can bunion exercises help reduce stress on a Morton’s neuroma?
The short answer is yes, but it is not always as simple.
Evidence suggests exercise can improve pain and some measures of hallux valgus, particularly in mild-to-moderate cases.
However, this is different from saying that bunion exercises have been proven to treat Morton’s neuroma.
So what we can therefore assume is that by improving the foot mechanics and load, we may reduce stress on the neuroma site, assisting the body’s natural recovery.
Exercises may include:
- controlled big-toe movement
- exercises to improve intrinsic foot muscle control
- toe spreading exercises
- strengthening exercises for the foot
- controlled calf and ankle exercises
- balance exercises
- progressive weight-bearing exercises
- exercises that improve the way the foot controls load during walking
And there is no one-size-fits-all.
What we should focus on too is the ability and capacity of the individual, and then work on what they are missing out on.
As an example, forcing the big toe into a position with a toe separator simply because someone has a bunion is not necessarily appropriate, and it may not create the desired change anyway.
The aim is not to “push the bunion back into place”.
The aim here is to improve the available movement and control of the foot and help the person tolerate load more effectively, yes, starting from the big toe, if a bunion is present, but the focus has to be also on the other toes, as well as the ankle.
Can big toe mobility affect pressure on a Morton’s neuroma?
For what we know, the big toe plays an important role during walking, particularly during the later part of stance.
For simplicity, we expect that the big toe can passively extend between 40° and 65° for functional walking or running patterns.
That’s when the metatarsophalangeal joint needs to move as the body progresses over the foot. We have already seen this concept in the ankle-knee mechanics.
So, as a consequence, if the big toe and first ray do not function well, the body can modify how it moves through the forefoot by shifting the weight to the lateral portion of the foot, which we can summarise with:
Big toe mobility may influence how load is transferred through the forefoot.
But this should not be interpreted as:
“More big toe mobility automatically means less pressure on a Morton’s neuroma.”
That has not been established by the individual presentation.
So the goal is not simply to make the big toe or first ray “more mobile”, but the goal has to be to determine whether the person has an appropriate combination of:
mobility + strength + control + load tolerance with their feet and ankle.
What about stretching the big toe?
Stretching a tissue to a desired position is not a fix.
Indeed, the big-toe mobility exercises may be useful when a person has a genuine mobility restriction, and not just because they present with a bunion.
To implement these mobility exercises, we have to work with comfortable and controlled movement, going for a step-by-step approach based on the individual’s current presentation and potential goals, which differ from repeatedly forcing the toes into painful positions, which may only aggravate the presentation and the individual’s pain level.
Let’s not forget that with Morton’s neuroma, the priority is usually to reduce irritation rather than repeatedly provoking the painful area.
This is particularly important during an acute flare.
A rehabilitation program may therefore start with comfortable movements and gradually progress towards weight-bearing activities as symptoms allow.
What works best for reducing Morton’s neuroma irritation?
There is no single treatment that works best for every person.
The evidence supports a range of approaches, and treatment should depend on the severity and duration of symptoms.
1. Reduce mechanical compression
This is one of the most important principles. Footwear that compresses the forefoot can increase mechanical stress around the metatarsal region.
So changing to footwear with a wider shoe box, which means more room around the toes, can be useful.
This supports the idea that redistributing load can be an important part of conservative management.
2. Consider metatarsal support
Metatarsal pads or appropriately designed orthoses may help redistribute pressure away from the painful area and the position of the pad does matters. In fact, a metatarsal pad is generally positioned proximal to the metatarsal heads rather than directly underneath the painful neuroma.
That said, not every person responds to the same orthotic approach; each individual case has to be evaluated before thinking of what fits all.
3. Temporarily reduce aggravating load
Being aware of what makes the Morton’s neuroma symptoms worst, like running, jumping, or particular shoes, is important. Because changing this habit, to start with, can help reduce the aggravating exposure, and it may allow symptoms to settle.
And this does not necessarily mean complete rest and doing nothing. Indeed, the aim is often to find a level of activity that the foot can tolerate without repeatedly provoking symptoms, and from there build tolerance and load.
4. Exercise and rehabilitation
Exercise can be useful when the goal is to improve foot strength, control, mobility and overall load tolerance, but exercise should not be used simply to “fix” the bunion and hope the neuroma gets better. The objective here is to improve how the person uses the foot.
For someone with both hallux valgus and Morton’s neuroma, rehabilitation may therefore involve the big toe, foot muscles, ankle, calf and the way the entire lower limb manages load.
What about inflammation?
The word “inflammation” is commonly used when discussing Morton’s neuroma, but despite the acute phase of the presentation, it would be better to describe it as a painful enlargement and irritation of a plantar digital nerve, with mechanical compression playing an important role.
And why this is helpful to know is because we can distinguish between:
reducing inflammation
and
reducing mechanical irritation of the nerve.
Reducing mechanical irritation is often a major part of conservative management, but that said, in more chronic cases, the use of medication or corticosteroid injection may also be considered depending on the clinical situation.
Corticosteroid Injections for Morton’s Neuroma
Corticosteroid injections overall can be a useful conservative method for pain reduction for Morton’s Neuroma.
A systematic review of infiltrative treatments published in 2024 reported that corticosteroids, among other injection treatments, were associated with reductions in Morton’s neuroma pain. But of course, this is not a permanent fix, and it may not work the same for everyone and more specifically, this is not going to change the bunion, improve footwear tolerance or foot strength or address an underlying load-management problem.
So yes, for some people, it can be useful as part of a broader treatment plan rather than as the only intervention.
When should you get your foot assessed?
Now, in terms of assessment and further investigation, especially scans, I would always consider what the individual client presents with.
If the burning, tingling, numbness or sharp pain between the toes is not reduced via rest and conservative treatment within a time frame of 12 weeks, then it is worth going for a scan.
This is because several conditions can produce similar symptoms.
And this is particularly important when a person has both a bunion and forefoot nerve symptoms because the treatment needs to consider the whole mechanical picture rather than focusing only on the painful spot.
In conclusion, if you are suspicious of a neuroma presentation and you need assistance with your feet mobility, strength and lower limb movement capacity, here at Melbourne Massage and Treatment in Coburg, via Myotherapy treatment, I focus on individual presentation, and we would assess what your feet are lacking in, and what exercises and conservative treatment may work best for your presentation.
Book a Myotherapy treatment now for Morton's Neuroma recovery
Giovanni La Rocca
Giovanni moved to Melbourne, Australia, from Italy in 2008 and became a citizen in 2017. He started studying massage therapy in 2016, then completed a Bachelor of Health Science in Clinical Myotherapy in August 2024. During those years, he also specialised in Thai Massage and Manual Lymphatic Drainage for presentations like Lipoedema and Lymphoedema and recovery from Cosmetic Surgery. Nowadays, he runs his clinic in Coburg, Melbourne, where he integrates movement therapy into his practice to enhance overall well-being. He also values meditation, having completed several Vipassana courses. Committed to continuous learning, he aims to share his expertise in integrated therapies to help others achieve balance and resilience.